

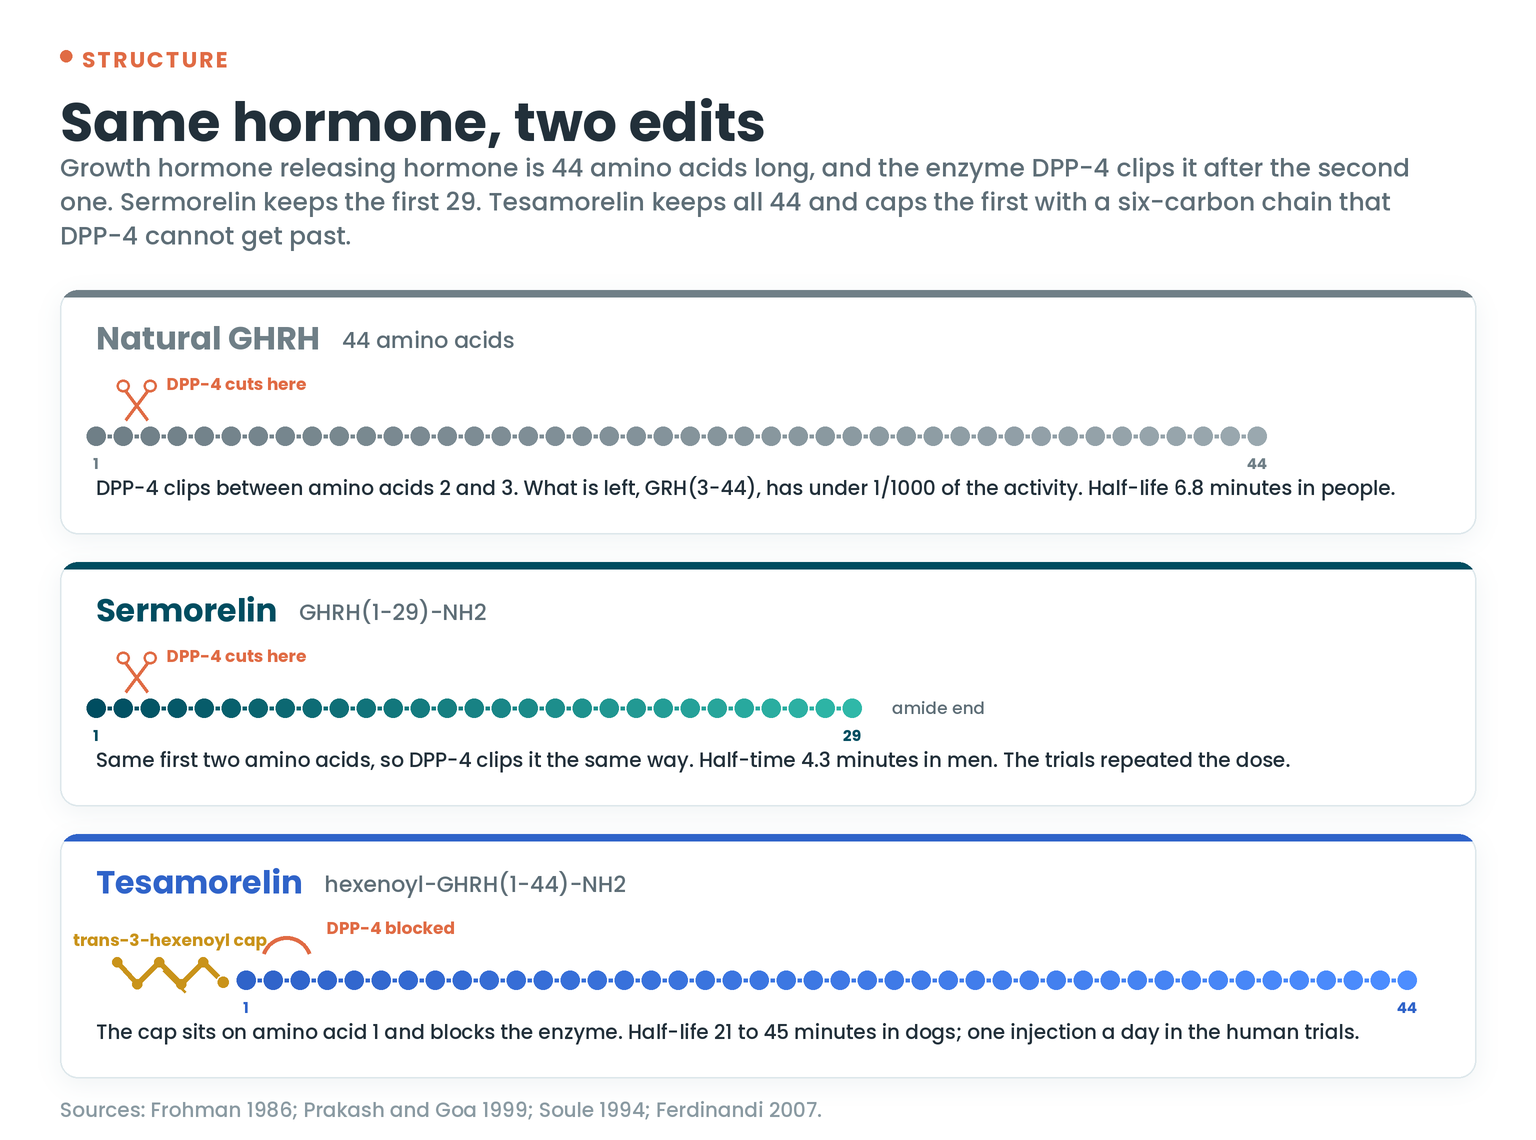
Tesamorelin and sermorelin are two edits of the same molecule. Your hypothalamus makes growth hormone releasing hormone, GHRH, as a chain of 44 amino acids, and an enzyme in your blood takes it apart within minutes. Sermorelin answers that by keeping only the first 29 amino acids, the shortest piece that still works. Tesamorelin keeps all 44 and puts a cap on the end the enzyme attacks.
That one design choice sets how long each peptide lasts, what its trials were able to measure, and which numbers belong to which name. Here is the comparison, edit by edit.
The Hormone They Are Both Cut From
GHRH is the signal your hypothalamus sends to the pituitary. It lands on the GHRH receptor on somatotroph cells, and the cells answer by making and releasing growth hormone. For the whole family of peptides built on it, see our guide to growth hormone peptides.
In 1986, Lawrence Frohman’s lab worked out what happens to the hormone once it is in the blood. An enzyme called dipeptidyl peptidase IV, DPP-4 for short, snips the bond between the second and third amino acids, alanine and aspartate. What is left, GRH(3-44), has less than one thousandth of the activity of the full hormone. Measured in people after an intravenous dose, the intact hormone had a half-life of 6.8 minutes.
The activity sits at the start of the chain. The first 29 amino acids are the shortest fragment that keeps full activity, and anything past that can go. Those two facts, a vulnerable start and a disposable tail, are where the two peptides part ways.
Sermorelin: The Short Cut
Sermorelin is GHRH(1-29)-NH2, the first 29 amino acids of the hormone with an amide group on the end. The sequence is YADAIFTNSYRKVLGQLSARKLLQDIMSR, and it begins with the same tyrosine and alanine as the natural hormone, so DPP-4 treats it the same way.
Soule’s group infused it into ten healthy men and timed its disappearance: a half-time of 4.3 minutes, with a metabolic clearance rate of 39.7 mL per kilogram per minute. Under the skin, the losses start before the peptide reaches the blood. In rats, about 4% of a subcutaneous dose of GHRH(1-29) made it into the circulation intact.
The design is deliberately minimal. Sermorelin keeps the part that works, accepts the short life, and its trials made up for that by repeating the dose, twice a day in some studies and nightly for months in others. The other way to lengthen the same 29-amino-acid chain, by hooking it to albumin, is the subject of sermorelin vs CJC-1295.
Tesamorelin: The Cap
Tesamorelin keeps the full 44-amino-acid sequence of human GHRH, amide end included, and adds one thing: a trans-3-hexenoyl group, a six-carbon chain with a single double bond, attached to the first amino acid, tyrosine. Its development code was TH9507, and the team that characterized it described the molecule as minimally modified.
That one addition made the peptide resistant to DPP-4. In rat, dog and human plasma it broke down more slowly than natural GHRH, and in dogs the apparent elimination half-life ran 21 to 45 minutes. Daily injections raised growth hormone and IGF-1 in pigs, rats and dogs at doses up to 600 µg/kg.
In people, a population pharmacokinetic analysis of 38 HIV-positive patients and healthy volunteers on 1 or 2 mg a day for 14 days put plasma clearance at 1,060 liters an hour with a volume of distribution of 200 liters. Age, body size, race and health status made no difference to those numbers. Our standalone piece on tesamorelin goes deeper on the molecule itself.
How the Enzyme Decides the Difference
Everything above comes down to one encounter: DPP-4 meets the first two amino acids of the chain. Step through what happens to the natural hormone, to sermorelin and to tesamorelin.
One enzyme, three chains
Step through what DPP-4 does to each one
STEP1
What the Human Trials Measured
Tesamorelin: Belly Fat, Liver Fat, Cognition and Blood Sugar
Tesamorelin’s main evidence is two 26-week phase 3 trials in 806 adults with HIV and excess abdominal fat, pooled in 2010. Everyone got 2 mg a day or placebo, and visceral fat, the deep fat around the organs, was measured on CT scans. At 26 weeks it fell by 24 cm² on tesamorelin against a 2 cm² gain on placebo, a treatment effect of 15.4%, while fat under the skin of the abdomen stayed put. Triglycerides dropped 37 mg/dL against a 6 mg/dL rise, and IGF-1 rose by 108 ng/mL. People who stayed on for a full year held a 17.5% visceral fat reduction and lost 3.4 cm off the waist. In the extension phases, those switched from tesamorelin to placebo regained the fat.
The 12-week dose-ranging trial that preceded phase 3 enrolled 61 patients on 1 mg, 2 mg or placebo. IGF-1 rose 48% on 1 mg and 65% on 2 mg, trunk fat fell 4.6% and 9.2% against a 0.8% gain on placebo, and lean body mass improved on both doses.
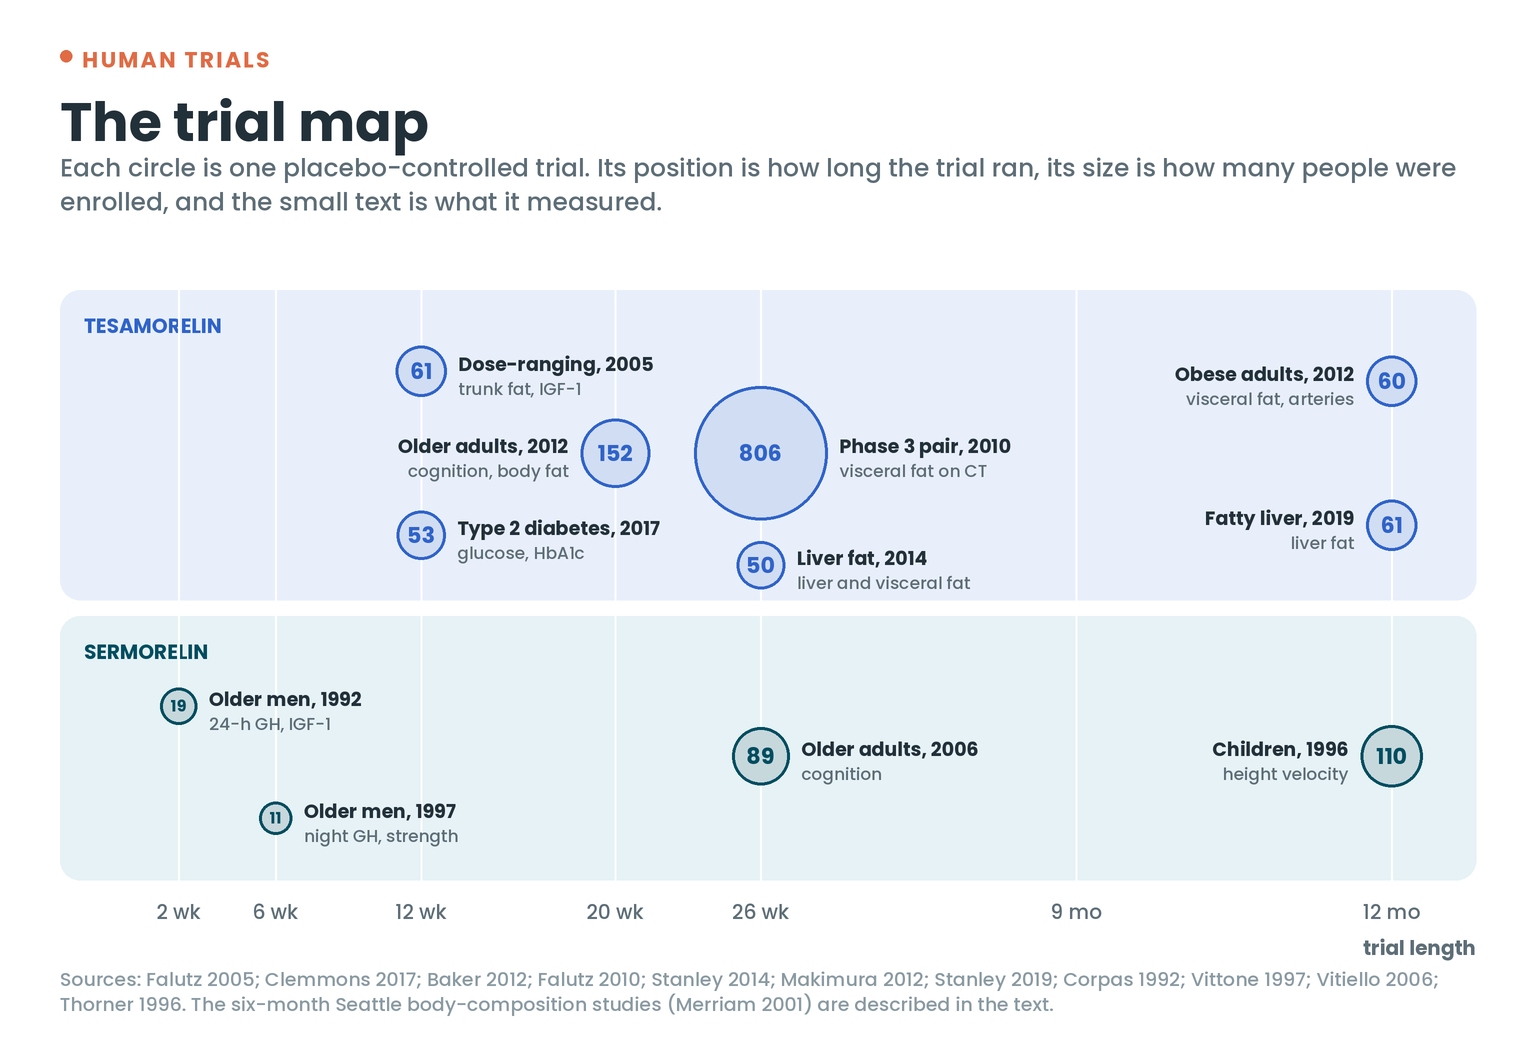
Outside HIV, 60 abdominally obese adults with low growth hormone output took tesamorelin or placebo for 12 months: visceral fat fell 16 cm² against a 19 cm² gain, with triglycerides, C-reactive protein and carotid artery wall thickness improving. In Laura Baker’s 20-week trial, 152 adults aged 55 to 87, 66 of them with mild cognitive impairment, injected 1 mg or placebo 30 minutes before bed. The tesamorelin group scored better on a cognitive composite, with the clearest gain in executive function, while IGF-1 rose 117% and stayed within the physiological range and body fat fell 7.4%.
Liver fat has two trials. A 50-person study at Massachusetts General Hospital found tesamorelin reduced liver fat over six months alongside the visceral fat loss. Takara Stanley’s follow-up put 61 people with HIV and fatty liver disease on 2 mg or placebo for 12 months: liver fat fell by an absolute 4.1 percentage points, a relative 37%, and 35% of the tesamorelin group finished with a liver fat fraction under 5% against 4% on placebo.
Because growth hormone pushes blood sugar up, every one of these trials tracked it. Across the phase 3 data there were no clinically meaningful glucose differences at 26 or 52 weeks. In the 50-person liver trial, fasting glucose rose 9 mg/dL at two weeks and then settled, with no difference at six months. In 53 people with type 2 diabetes, 12 weeks at 1 or 2 mg left insulin response, fasting glucose and HbA1c unchanged, and total and non-HDL cholesterol fell on 2 mg. In Baker’s trial, fasting insulin rose 35% within the normal range in the adults with mild cognitive impairment, and held steady in the healthy ones.
Sermorelin: Growth Hormone, Body Fat, Cognition and Growth in Children
Sermorelin’s adult trials are smaller and older, and they measured the hormone axis itself first. Corpas gave ten men with an average age of 68 either 0.5 mg or 1 mg under the skin twice a day for 14 days, with nine men in their twenties as the reference group. On the higher dose, 24-hour growth hormone and IGF-1 climbed until they were no longer different from the young men’s, with no change in fasting glucose, blood pressure or blood counts. Vittone gave 2 mg at bedtime for six weeks to eleven men aged 64 to 76: night-time growth hormone and pulse amplitude rose, pulse frequency and IGF-1 stayed where they were, two of six strength tests improved, and the authors concluded that one nightly dose does less than several doses through the day.
The longest adult work came from George Merriam and Michael Vitiello’s group in Seattle. In two six-month studies of healthy older women and men, nightly injections raised IGF-1 by about 30% in men and 23% in women not taking estrogen. Lean mass rose and body fat fell 5 to 8%, with the biggest change in visceral fat, and sleep quality was unchanged. Their cognition study put 89 healthy adults with an average age of 68 on six months of daily GHRH or placebo, and the GHRH group improved on five measures including the performance half of the WAIS-R intelligence test.
The biggest sermorelin trial was in children. Thorner’s group gave 110 growth-hormone-deficient children 30 µg/kg at bedtime for a year. Height velocity went from 4.1 cm a year to 8.0 at six months and 7.2 at twelve, 74% were classed as good responders, and bone age advanced in step with height age.
Tesamorelin vs Sermorelin Side by Side
| Tesamorelin | Sermorelin | |
|---|---|---|
| Built from | GHRH(1-44), the whole hormone | GHRH(1-29), the first 29 amino acids |
| The edit | A trans-3-hexenoyl cap on the first amino acid | The last 15 amino acids removed |
| What DPP-4 does to it | Blocked by the cap | Clips it like the natural hormone |
| Time in the body | Half-life 21 to 45 minutes in dogs; cleared at 1,060 L/h in people | Half-time 4.3 minutes in men |
| Receptor | GHRH receptor | GHRH receptor |
| Largest trial | 806 adults with HIV, 26 weeks, visceral fat on CT | 110 children, 12 months, height velocity |
| Headline result | Visceral fat −15.4% vs placebo at 26 weeks; liver fat −37% at 12 months | 24-hour growth hormone and IGF-1 restored to young-adult levels in older men after 14 days |
| Research doses | 1 or 2 mg once daily | 0.5 to 2 mg once or twice daily in adults; 30 µg/kg nightly in children |

Side Effects Recorded in the Trials
Tesamorelin’s record is the larger one because its trials were larger. Across 806 people in phase 3, the drug was described as generally well tolerated, and the rate of adverse events in the extension year matched the first 26 weeks. In the 12-month liver trial, injection-site complaints were more common on tesamorelin than placebo, and none were judged serious. In Baker’s older adults, 68% of the tesamorelin group reported a mild adverse event against 36% on placebo. In the four-month animal toxicology work, dogs given daily injections showed reversible liver, kidney and blood-count changes that the authors tied to sustained, above-normal growth hormone and IGF-1 rather than to the peptide itself.
Sermorelin’s record spans children and adults. In the review of its use in children, single intravenous doses and repeated daily injections were well tolerated, with brief facial flushing and pain at the injection site the most common events. Thorner’s year-long study found no adverse changes in blood chemistry or hormones and no excessive rise in IGF-1. Among older adults, Corpas saw no change in fasting glucose, blood pressure or blood counts over 14 days, Vittone saw no change in the glucose or insulin response to an oral glucose load over six weeks, and Merriam’s six-month studies listed mild fluid retention as the main side effect.
What the Two Share
Both peptides use the GHRH receptor, so the first step is identical: the pituitary is told to make and release its own growth hormone. The rhythm stays the body’s. Vittone’s older men on sermorelin kept their pulse frequency and got bigger pulses, and the tesamorelin pharmacokinetic work describes it as raising both basal and pulsatile secretion.
Both also sit inside the same feedback loop. Growth hormone raises IGF-1, IGF-1 raises somatostatin tone, and somatostatin pushes back on the pituitary. IGF-1 stayed within the physiological range through Baker’s 20-week trial, and Thorner’s children showed no excessive rise over a year.
And both bring only the GHRH half of a two-signal system. In 1990, Cyril Bowers showed in healthy men that GHRH plus a ghrelin-type peptide released more growth hormone than either alone, with the combination larger than the sum of the parts. That finding is why both peptides get paired with ipamorelin, a pairing we cover in ipamorelin vs sermorelin and tesamorelin vs ipamorelin.
Doses Used in the Research
- Tesamorelin: 2 mg once daily under the skin in the phase 3 trials, the 12-month obesity trial and both liver trials; 1 mg daily in the cognition trial and as the lower arm in the dose-ranging and diabetes trials.
- Sermorelin in adults: 0.5 mg or 1 mg under the skin twice daily for 14 days (Corpas); 2 mg once at bedtime for 6 weeks (Vittone); once-nightly injections for 6 months (Merriam, Vitiello). As a diagnostic test of pituitary reserve, 1 µg/kg intravenously.
- Sermorelin in children: 30 µg/kg under the skin at bedtime for 12 months (Thorner).
- In animals: tesamorelin up to 600 µg/kg daily by vein or under the skin in pigs, rats and dogs (Ferdinandi); GHRH(1-29) given to rats by both routes to measure how much survives subcutaneous injection (Rafferty).
FAQ
Is tesamorelin just a longer-lasting sermorelin?
They act on the same receptor and carry the same first 29 amino acids, so the pituitary gets the same instruction. Tesamorelin keeps the remaining 15 amino acids and adds a cap that stops DPP-4, and its trials ran on one injection a day while sermorelin’s used twice-daily or nightly dosing.
Which one has more human data?
Tesamorelin, by a wide margin: 806 people in the phase 3 pair alone, plus trials of 61, 60, 152, 50, 61 and 53 people measuring fat on CT, liver fat on MR spectroscopy, cognition and blood sugar. Sermorelin’s largest trial is 110 children; its adult studies ran from 10 to 89 people.
Which one targets belly fat?
Tesamorelin is the one measured on CT: a 15.4% visceral fat reduction versus placebo at 26 weeks, with fat under the skin unchanged. Sermorelin’s six-month studies recorded a 5 to 8% drop in body fat with the biggest change in visceral fat, measured in healthy older adults.
Do the results last after stopping?
In the tesamorelin extension phases, people switched to placebo regained the visceral fat they had lost within 26 weeks, which is the clearest measurement so far of what happens when a GHRH analog stops.
Does either one raise blood sugar?
In 52 weeks of phase 3 data and a 12-week trial in people with type 2 diabetes, tesamorelin produced no meaningful change in glucose or HbA1c. Sermorelin left fasting glucose unchanged in older men over 14 days and in children over a year.
How is sermorelin different from CJC-1295?
CJC-1295 is the same 29-amino-acid chain with four amino acids swapped and a hook that binds it to albumin, which stretches its half-life from minutes to days. Tesamorelin solves the same problem a different way, by capping the full 44-amino-acid hormone.
References
- Frohman LA, et al. Rapid enzymatic degradation of growth hormone-releasing hormone by plasma in vitro and in vivo to a biologically inactive product cleaved at the NH2 terminus. J Clin Invest. 1986;78(4):906-913. DOI
- Prakash A, Goa KL. Sermorelin: a review of its use in the diagnosis and treatment of children with idiopathic growth hormone deficiency. BioDrugs. 1999;12(2):139-157. DOI
- Soule S, et al. Incorporation of D-Ala2 in growth hormone-releasing hormone-(1-29)-NH2 increases the half-life and decreases metabolic clearance in normal men. J Clin Endocrinol Metab. 1994;79(4):1208-1211. DOI
- Rafferty B, et al. Growth hormone-releasing factor analogue (hGRF1-29NH2): immunoreactive-GRF plasma levels after intravenous and subcutaneous administration. J Endocrinol. 1985;107(3):R5-R8. DOI
- Ferdinandi ES, et al. Non-clinical pharmacology and safety evaluation of TH9507, a human growth hormone-releasing factor analogue. Basic Clin Pharmacol Toxicol. 2007;100(1):49-58. DOI
- González-Sales M, et al. Population pharmacokinetic analysis of tesamorelin in HIV-infected patients and healthy subjects. Clin Pharmacokinet. 2015;54(3):285-294. DOI
- Falutz J, et al. Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in HIV-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials with safety extension data. J Clin Endocrinol Metab. 2010;95(9):4291-4304. DOI
- Falutz J, et al. Effects of tesamorelin, a growth hormone-releasing factor, in HIV-infected patients with abdominal fat accumulation: a randomized placebo-controlled trial with a safety extension. J Acquir Immune Defic Syndr. 2010;53(3):311-322. DOI
- Falutz J, et al. Long-term safety and effects of tesamorelin, a growth hormone-releasing factor analogue, in HIV patients with abdominal fat accumulation. AIDS. 2008;22(14):1719-1728. DOI
- Falutz J, et al. A placebo-controlled, dose-ranging study of a growth hormone releasing factor in HIV-infected patients with abdominal fat accumulation. AIDS. 2005;19(12):1279-1287. DOI
- Makimura H, et al. Metabolic effects of a growth hormone-releasing factor in obese subjects with reduced growth hormone secretion: a randomized controlled trial. J Clin Endocrinol Metab. 2012;97(12):4769-4779. DOI
- Baker LD, et al. Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults: results of a controlled trial. Arch Neurol. 2012;69(11):1420-1429. DOI
- Stanley TL, et al. Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation: a randomized clinical trial. JAMA. 2014;312(4):380-389. DOI
- Stanley TL, et al. Effects of tesamorelin on non-alcoholic fatty liver disease in HIV: a randomised, double-blind, multicentre trial. Lancet HIV. 2019;6(12):e821-e830. DOI
- Clemmons DR, et al. Safety and metabolic effects of tesamorelin, a growth hormone-releasing factor analogue, in patients with type 2 diabetes: a randomized, placebo-controlled trial. PLoS One. 2017;12(6):e0179538. DOI
- Corpas E, et al. Growth hormone (GH)-releasing hormone-(1-29) twice daily reverses the decreased GH and insulin-like growth factor-I levels in old men. J Clin Endocrinol Metab. 1992;75(2):530-535. DOI
- Vittone J, et al. Effects of single nightly injections of growth hormone-releasing hormone (GHRH 1-29) in healthy elderly men. Metabolism. 1997;46(1):89-96. DOI
- Merriam GR, et al. Growth hormone releasing hormone treatment in normal aging. J Anti Aging Med. 2001;4(4):331-343. DOI
- Vitiello MV, et al. Growth hormone releasing hormone improves the cognition of healthy older adults. Neurobiol Aging. 2006;27(2):318-323. DOI
- Thorner M, et al. Once daily subcutaneous growth hormone-releasing hormone therapy accelerates growth in growth hormone-deficient children during the first year of therapy. J Clin Endocrinol Metab. 1996;81(3):1189-1196. DOI
- Bowers CY, et al. Growth hormone (GH)-releasing peptide stimulates GH release in normal men and acts synergistically with GH-releasing hormone. J Clin Endocrinol Metab. 1990;70(4):975-982. DOI
Stay sharp,
Joe Mars
The Peptide Report
P.S. If you’re weighing a peptide you inject once a day against one you inject twice, the Peptides and Biohacking Hub on Skool is where our members compare notes on what each schedule did for them. It’s free. Come join us.
